





Cervical myelopathy: spinal-cord warning signs, diagnosis and treatment
Cervical myelopathy is dysfunction of the spinal cord in the neck, commonly caused by degenerative compression. It may affect walking, balance, hand dexterity, strength and bladder or bowel function.
Unlike an isolated nerve-root problem, myelopathy can influence several limbs and long-tract functions. Symptoms may develop gradually and be mistaken for ageing, arthritis or peripheral neuropathy. Early recognition matters because neurological decline can become irreversible.
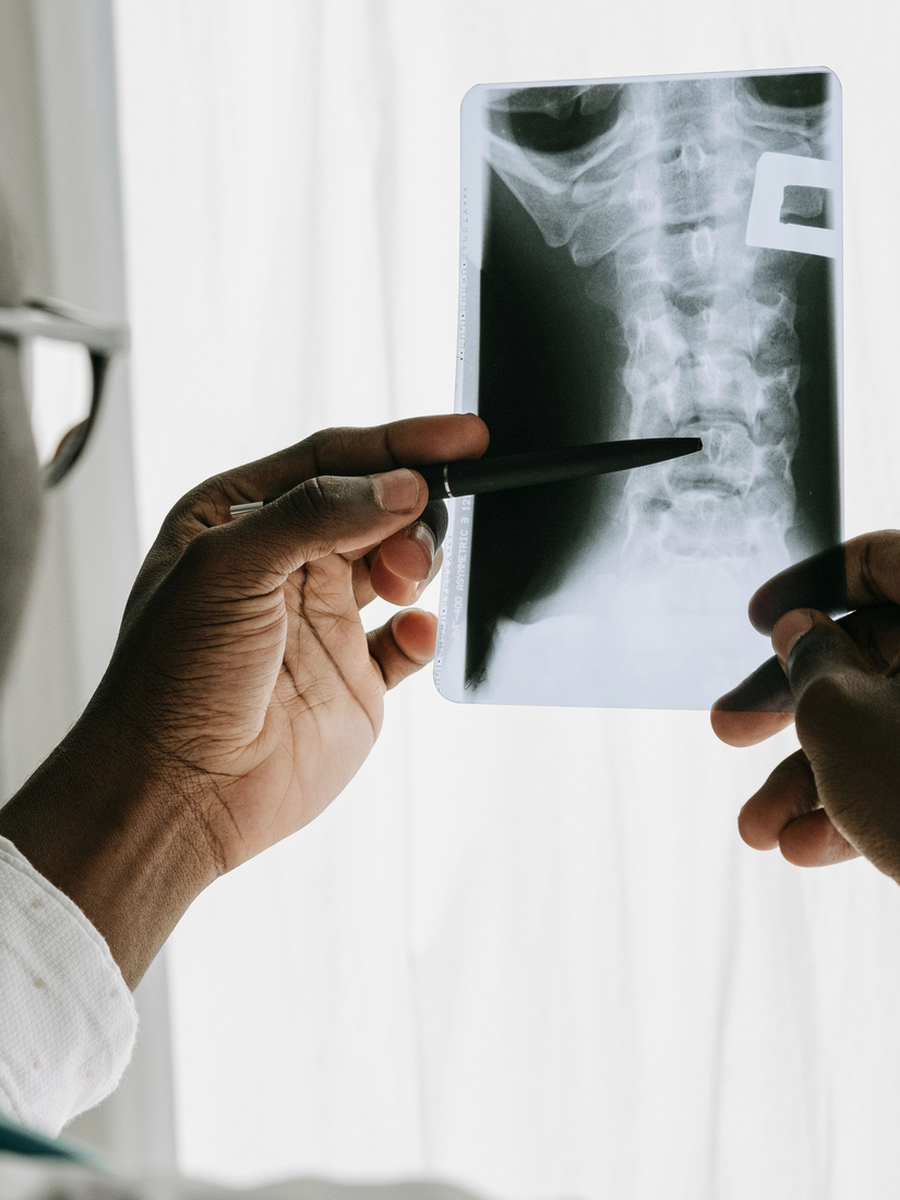
Assessment and differential diagnosis
The examination evaluates gait, balance, hand dexterity, reflexes, strength, sensation and upper motor-neuron signs. MRI is central to assessing spinal-cord compression and signal change. Alternative causes such as peripheral neuropathy, brain disease or vitamin deficiency may also require consideration.
| Clinical situation | Possible next step | Why it matters |
|---|---|---|
| Mild stable findings | Specialist assessment and close monitoring | Progression risk must be discussed. |
| Moderate or severe impairment | Surgical consultation | Decompression may be recommended. |
| Rapid deterioration | Urgent evaluation | Delay may threaten neurological recovery. |

Treatment and management
Conservative symptom treatment does not remove spinal-cord compression. For clinically significant degenerative cervical myelopathy, surgical decompression is often considered to prevent further decline. Rehabilitation may support function before and after surgery but should not delay appropriate referral.
Questions for shared decision-making
Before choosing care, ask the provider to explain the working diagnosis, expected outcome, alternatives and review point.
What is the target?
Identify the structure, mechanism or functional problem being addressed.
What outcome matters?
Define measurable goals for pain, walking, sleep, work or daily activity.
What are the alternatives?
Compare active care, medication, procedures, technology and surgery when relevant.
When should the plan change?
Set criteria for stopping, modifying or escalating care.

Related guides
Cervical spinal stenosis
Cervical disc herniation
Specialized external resources
These links lead to independent specialized websites and do not change the educational role of The Spine Page.
Clinique TAGMED
Clinical information about motorized spinal decompression and disc-related conditions.
SOS Sciatique
Focused guides about sciatica, nerve-root symptoms and warning signs.
Frequently asked questions
Is myelopathy the same as radiculopathy?
No. Myelopathy affects the spinal cord; radiculopathy affects a nerve root.
Can pain be mild?
Yes. Neurological dysfunction may be more important than pain.
What are early signs?
Hand clumsiness, gait imbalance and reflex changes may appear early.
Can it improve without surgery?
Some mild cases remain stable, but progression risk requires specialist discussion.
Why is MRI important?
It identifies cord compression and possible signal change.
Can physiotherapy remove compression?
No.
What is surgical decompression?
A procedure intended to create more space for the spinal cord.
Can surgery restore all function?
Not always, especially when deficits are long-standing.
Should manipulation be used over a compressed cord?
This requires extreme caution and appropriate medical assessment.
Does The Spine Page treat myelopathy?
No.
Sources consulted
- AO Spine — Degenerative Cervical Myelopathy Clinical Practice Guideline
- American College of Radiology — Cervical Pain or Cervical Radiculopathy
Last editorial review: July 2026. General educational information only.
Dr. Sylvain Desforges, B.Sc., D.O., N.D., osteopath — The Spine Page
Continue exploring spine health
Use the condition and treatment hubs to compare the next steps.
The Spine Page — The best treatments for your spinal problems — www.thespinepage.com