

Gradual biological reduction in the size of herniated disc material. It does not always track pain improvement exactly.
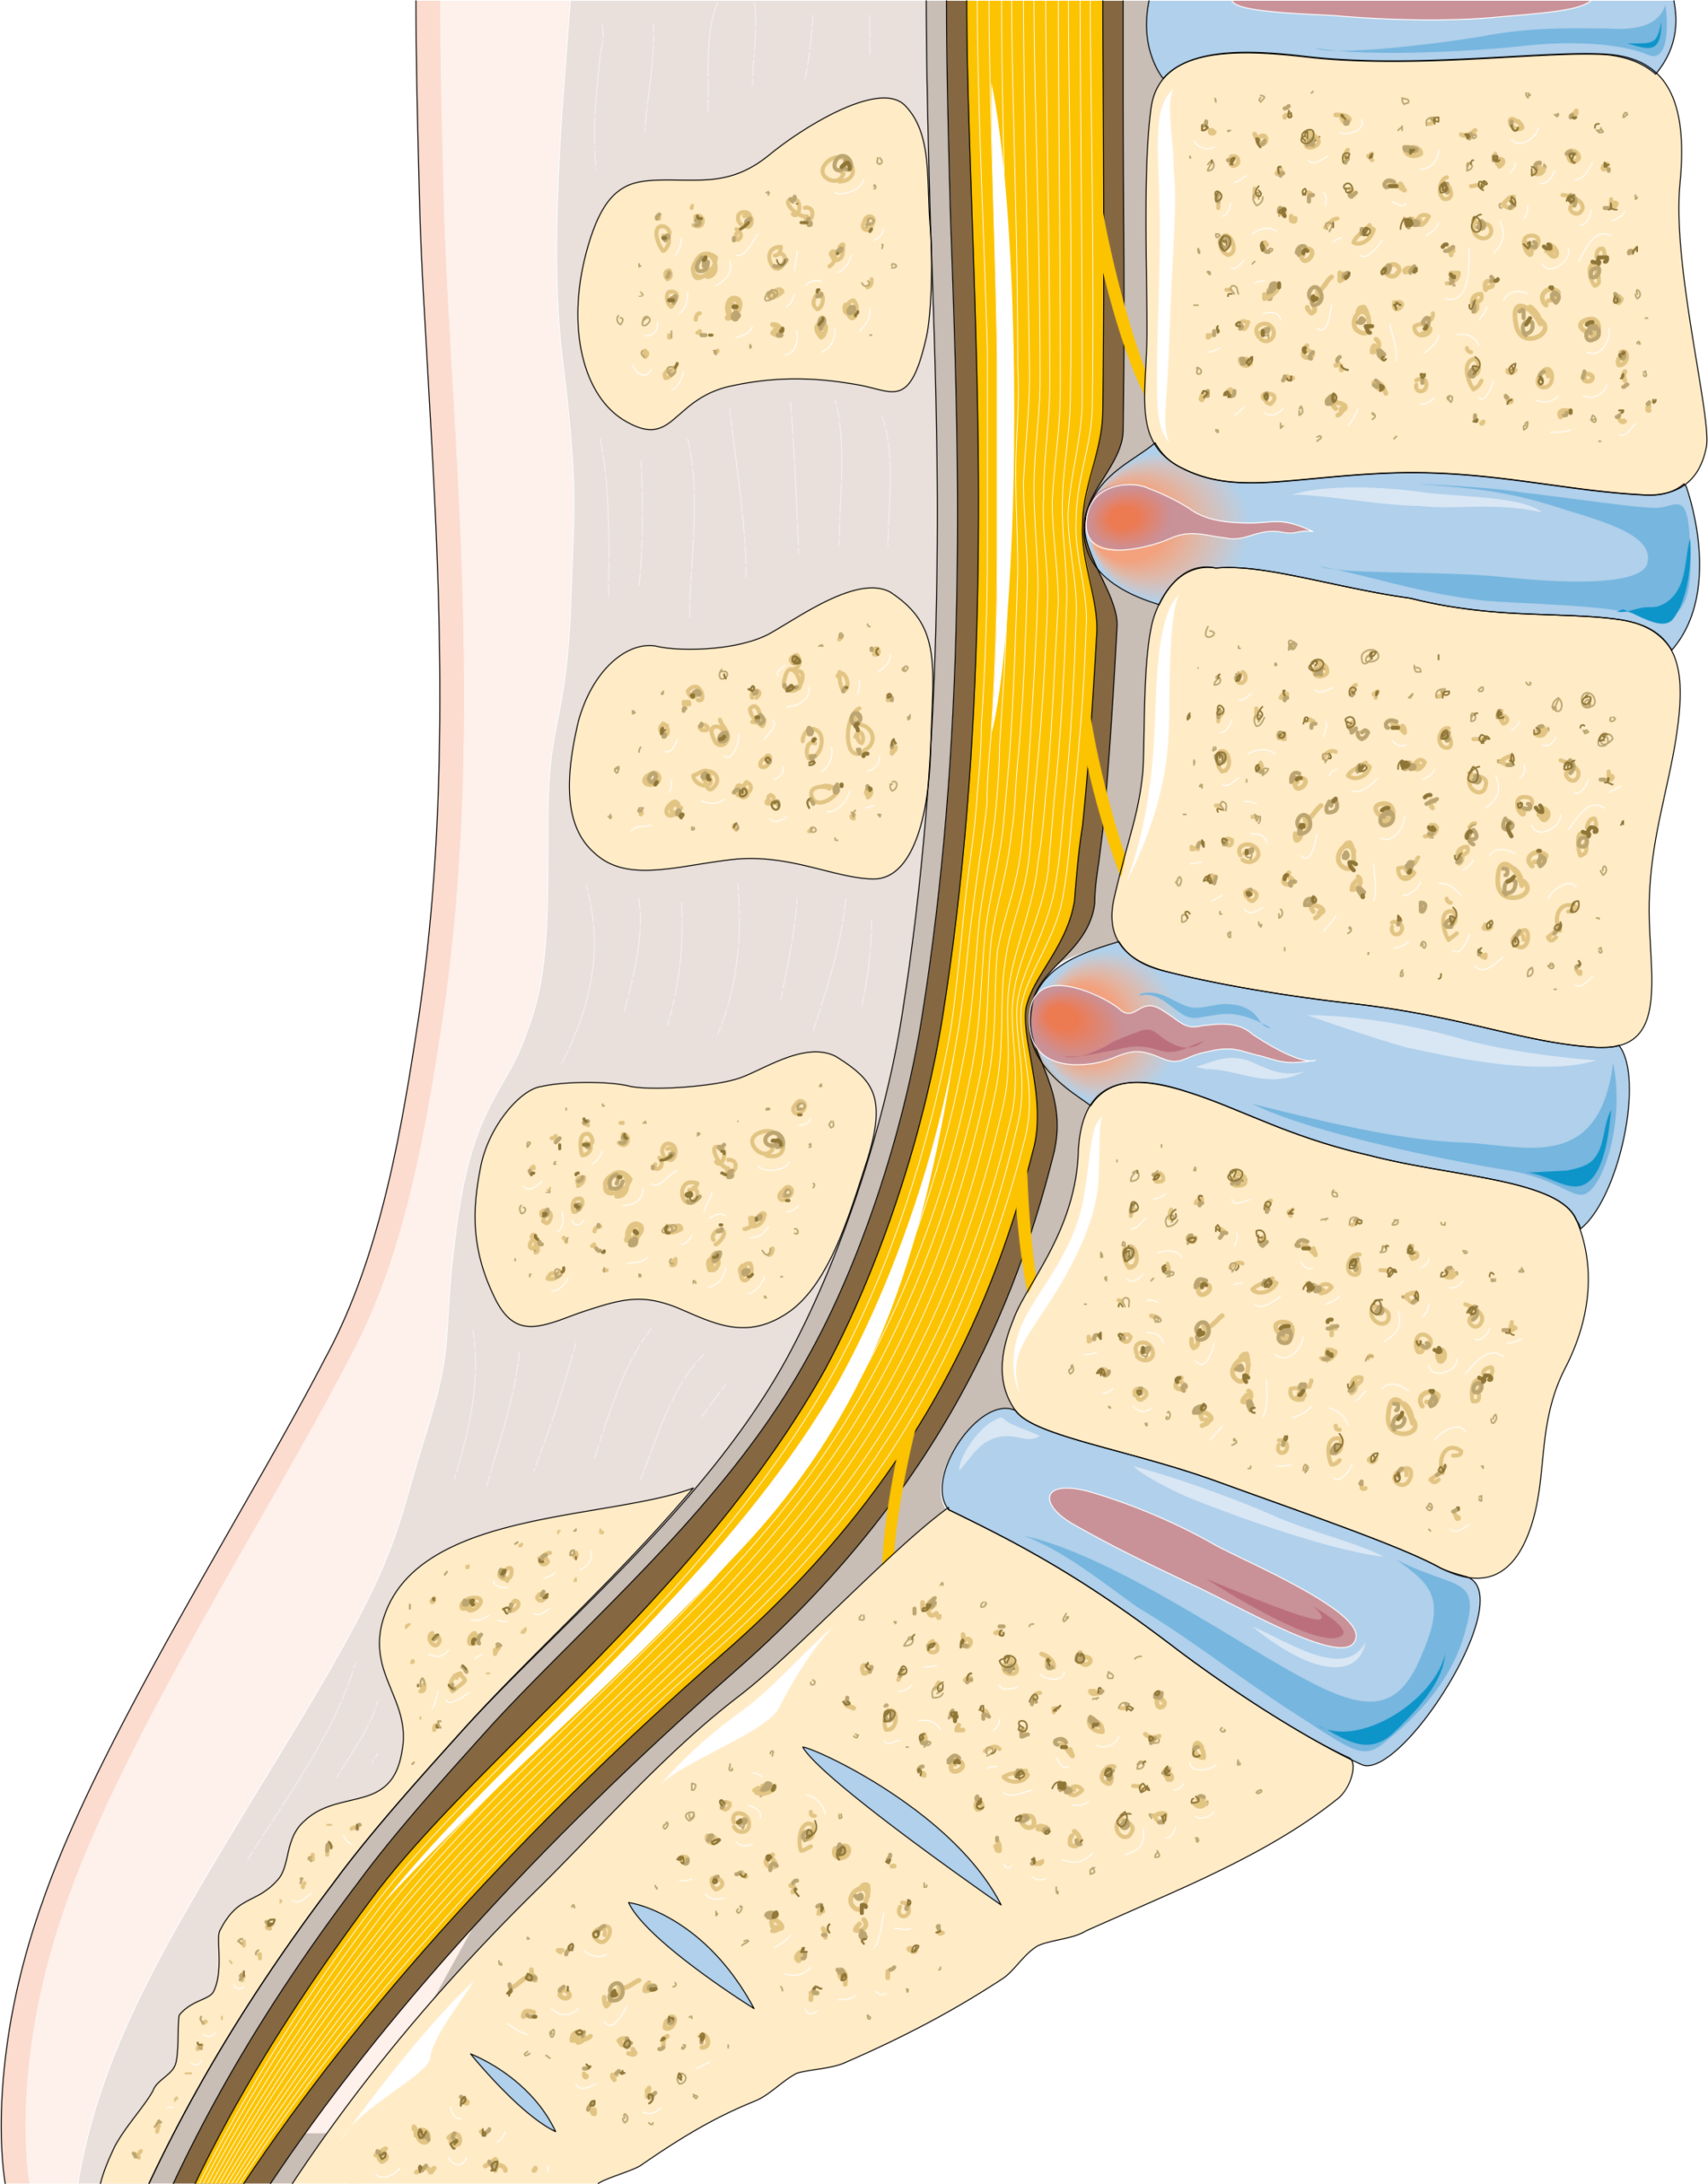
Laboratoires Servier / SMART-Servier Medical Art — CC BY-SA 3.0. Image source.

Understanding this term
In the context of herniation, resorption means a reduction in displaced disc material over time. Local immune activity, tissue breakdown and water-content changes can contribute. It does not mean complete regeneration of the original disc. Reduction is observed in some patients followed without surgery, but not in everyone.
Symptoms and assessment
Radiological regression and clinical improvement are not perfectly synchronized. Someone may improve while a herniation remains visible, or have symptoms despite shrinkage. Neurological follow-up remains necessary. Never wait for hypothetical resorption when weakness progresses or cauda equina signs appear.
Assessment considers symptom onset, distribution, restricted activities and medical history. Imaging findings must be compared with the clinical examination: a visible abnormality does not, on its own, establish the source of pain.
Management and outlook
Natural-history studies cannot attribute resorption to a single modality received during follow-up. Improvement after motorized decompression can have several explanations; it does not demonstrate suction or therapeutic superiority. Care is chosen on the basis of observable clinical benefit and safety.
For a mechanical problem without concerning findings, care aims for a gradual return to activity, individually selected exercises and measurable functional goals. Manual care may complement this approach when the examination supports it. Progress is judged through walking, sleep and daily tasks, as well as symptoms, rather than through an image alone.
When to seek prompt assessment
New or progressive weakness, newly impaired walking, loss of sensation around the saddle region, or new bladder or bowel control problems require urgent medical assessment.
Frequently asked questions
Does resorption put the fragment back into the disc?
Not necessarily: it may involve breakdown and reduction of the fragment.
Are repeated MRIs needed until it disappears?
Not routinely. Follow-up imaging should answer a useful clinical question.
Can imaging establish the diagnosis alone?
No. Findings must fit the clinical history and examination before they guide treatment.
Should all activity stop?
Usually not: loading is adjusted and gradually increased according to tolerance and the diagnosis.
How should progress be monitored?
Track functional abilities, neurological symptoms and resumed activities so care can be adjusted.
Concept diagram showing key relationships; this is not a scan or an anatomical drawing to scale.
Role of TAGMED care
TAGMED offers motorized spinal decompression, a form of traction. Initial assessment considers whether symptoms, neurological findings and imaging, when indicated, agree. The value of this approach remains uncertain depending on the condition; NICE recommends against offering traction for low back pain with or without sciatica. It does not guarantee disc resorption, disc repair or correction of stenosis. Alternatives, contraindications, functional goals and stopping criteria should be discussed before any trial.
Medical references
- Prospective observational study; Kesikburun et al.. Spontaneous regression of extruded lumbar disc herniation: correlation with clinical outcome (2019).
- American Association of Neurological Surgeons. Herniated Disc.
- American Association of Neurological Surgeons. Cauda Equina Syndrome.
- NICE. Low back pain and sciatica in over 16s: assessment and management (NG59).
References document the topic; their inclusion does not imply endorsement of TAGMED services by those organizations.
Educational information from The Spine Page. This entry does not replace an individual assessment. Documentary version: October 12, 2026. Sylvain Desforges, B.Sc., D.O., N.D., osteopath and naturopath.
TAGMED clinic contact details
For non-urgent consultations and information about available services.
Clinique TAGMED — Terrebonne
1150, rue Lévis, Suite 200
Terrebonne (Québec) J6W 5S6
450‑704‑4447
Clinique TAGMED — Montréal
1140, avenue Beaumont
Mont-Royal (Québec) H3P 3E5
1‑877‑672‑9060