





Spinal decompression for sciatica in Terrebonne: candidates and limitations
Motorized decompression is sometimes proposed for disc-related radicular pain, but it is not automatically appropriate for every case of sciatica.
Selection should verify the working diagnosis, contraindications, neurological stability, positional tolerance and measurable goals.
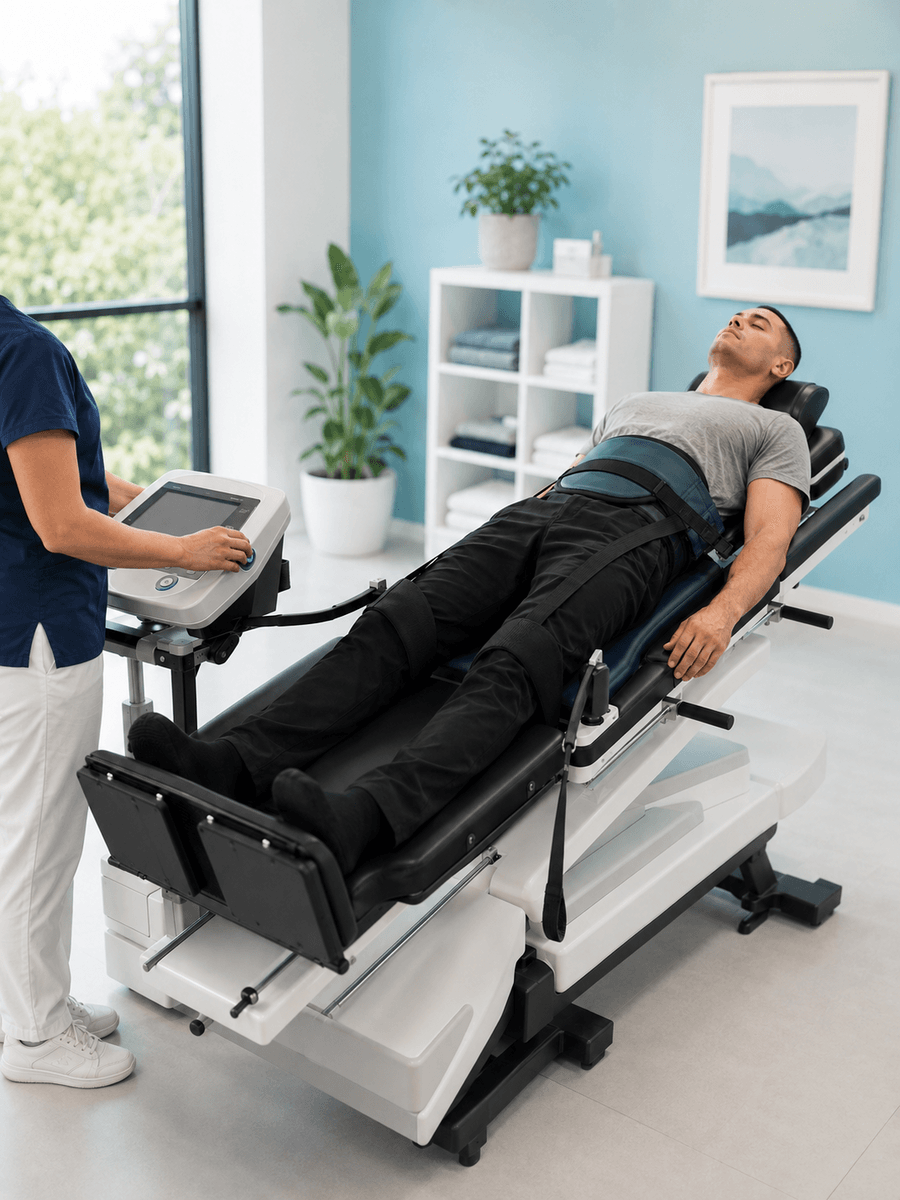
Clinical assessment and decision points
Fracture, instability, selected bone disease, severe compression with progressive deficit or an undiagnosed presentation may make this approach inappropriate.
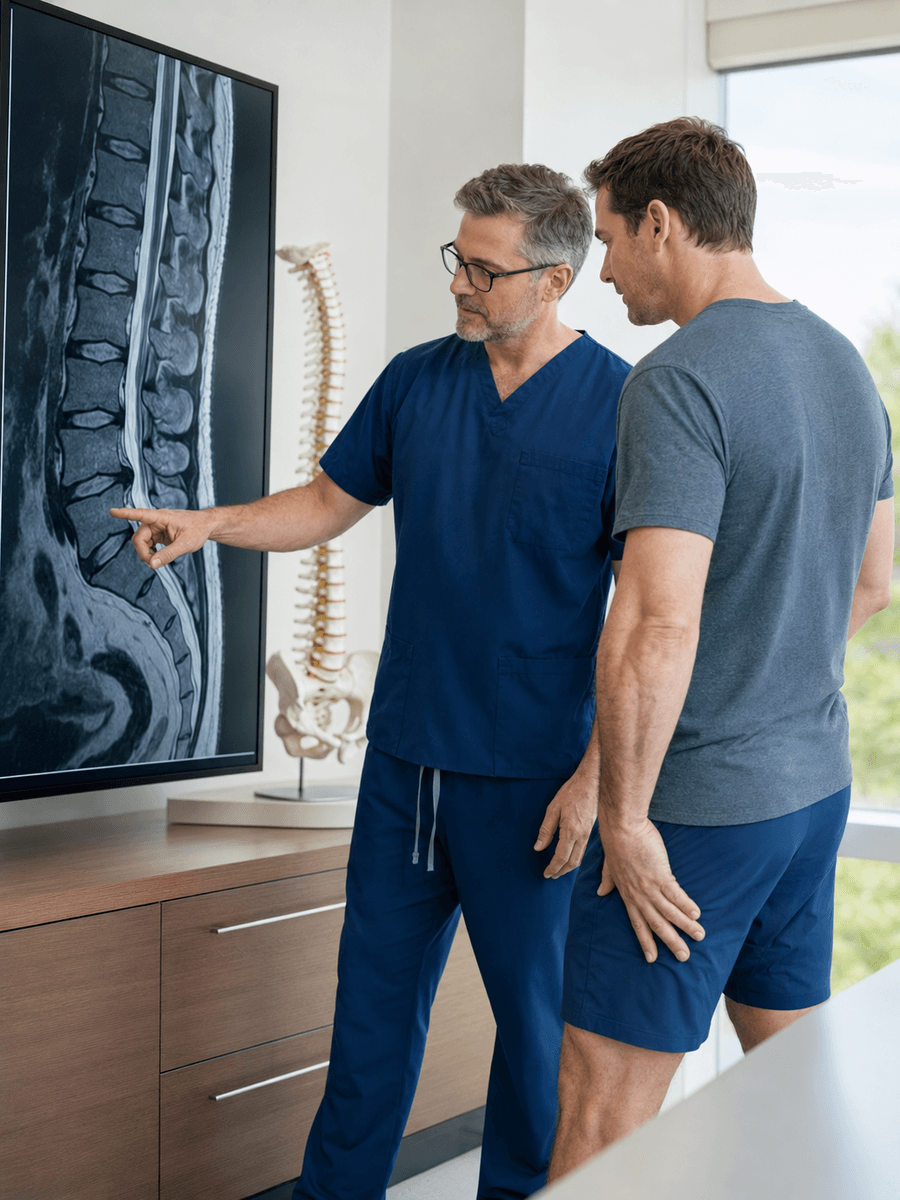
Examination compares strength, sensation, reflexes, gait, the hip and response to lumbar movement. Imaging is selected when it can change management, not merely to confirm that an abnormality exists.
| Clinical situation | Possible next step | Why it matters |
|---|---|---|
| Stable disc-related pattern | Individualized trial may be considered | Selection and monitoring remain essential. |
| Progressive weakness | Prompt medical referral | Passive technology must not delay escalation. |
| No measurable progress | Review diagnosis and strategy | Automatic repetition is not justified. |
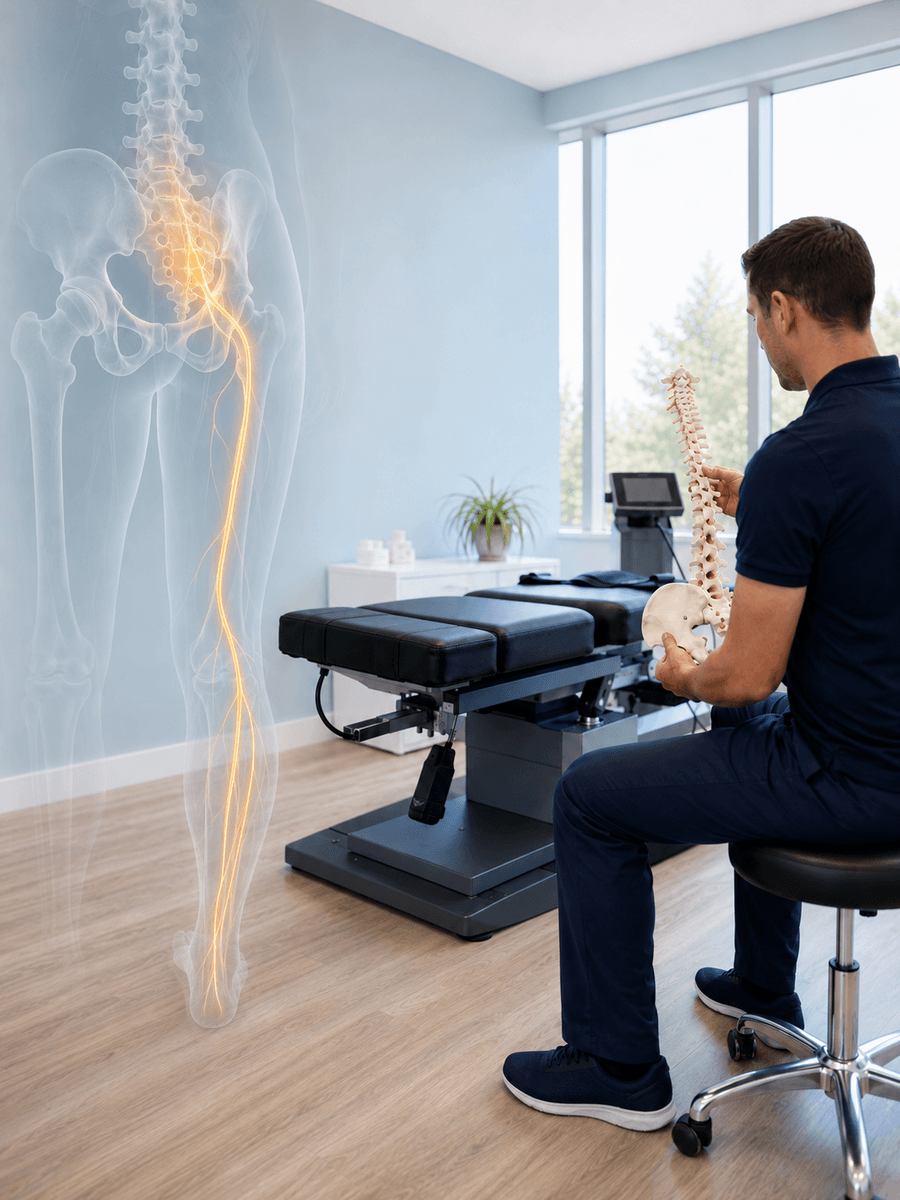
Management options in Terrebonne
When selected, decompression should fit within a plan that includes education, compatible activity, exercise and neurological follow-up rather than replacing every other component.
The plan must remain reviewable. Neurological worsening, lack of measurable progress or a new atypical finding should trigger reassessment rather than automatic repetition of the same treatment.
How to build a measurable plan
The protocol should document parameters, immediate tolerance, symptom distribution, walking, sleep and a formal review date.
Treatment value is judged by changes that matter to the person: better walking, sleep, work, driving or activity while maintaining neurological safety.
- Confirm the clinical indication.
- Screen contraindications.
- Set measurable goals.
- Document treatment parameters.
- Include an active strategy.
- Stop with neurological worsening.
Track progress and review the plan at the right time
A credible plan defines expected changes and a review point before care begins. Pain intensity alone is insufficient. Symptom distribution, strength, sensation, walking, sleep, positional tolerance and participation in meaningful activities provide a more complete picture of progress.
Temporary relief after treatment does not automatically confirm the proposed cause. Likewise, one more painful day does not necessarily mean that the condition is deteriorating. The trend over several days, function and neurological status should be interpreted together.
Establish a baseline
Record walking distance, sitting time, sleep, strength and one meaningful activity before starting care.
Set a review point
Decide when outcomes will be compared so an ineffective approach is not continued automatically.
Monitor neurological status
New weakness, spreading numbness or a gait change matters even when pain intensity decreases.
Compare pain and function
A person may report less pain without regaining capacity, or function better while some pain remains.
Review alternative causes
The hip, sacroiliac joint, a peripheral nerve or a systemic condition may occasionally mimic sciatica.
Escalate proportionately
Imaging, referral or a procedure should be considered when risk or functional loss justifies it.
Common errors to avoid
- Treating an MRI finding without checking whether it matches the side, symptom distribution and examination.
- Promising a fixed number of visits before establishing a working diagnosis and baseline measures.
- Confusing short-term relief with neurological or functional recovery.
- Repeating passive care despite no measurable progress in meaningful activities.
- Ignoring progressive weakness because pain fluctuates or is temporarily less intense.
- Delaying urgent assessment to finish a predetermined conservative program.
Shared decision-making is stronger when uncertainty is explained directly. Readers should understand what is confirmed, what remains probable, which alternatives are still possible and what changes would require a different plan. When symptoms persist or the diagnosis remains uncertain, a focused second opinion may be more useful than automatically adding another technique.
Questions to ask before starting care
What is the working diagnosis?
Ask which symptoms and examination findings support it.
Which outcome will be measured?
Walking, sleep, strength and meaningful activities matter as much as pain.
When will the plan be reviewed?
Set a time point and criteria to stop, change or escalate care.
Which alternatives remain possible?
Compare active care, technologies, procedures and specialist assessment.
Related Terrebonne cluster guides
Specialized local resource
This local resource is disclosed separately so readers can distinguish independent editorial information from clinical services.
Clinique TAGMED – Terrebonne
Description of assessment and non-surgical sciatica services available in Terrebonne.
Frequently asked questions
Is decompression the same as traction?
It uses distraction or traction forces, although some motorized devices vary cycles and parameters.
How many sessions are needed?
There is no universal number. Care should be individualized and reviewed using measurable outcomes.
Can it treat a disc herniation?
It is proposed for selected disc-related patterns, but it does not suit every herniation and does not guarantee anatomical change.
What should be monitored?
Symptom distribution, strength, sensation, walking, sleep and any neurological worsening.
Can it be combined with exercise?
An active graduated approach can be integrated according to tolerance and diagnosis.
When should treatment stop?
With neurological worsening, marked pain increase, adverse effects or no progress at the planned review.
Is an MRI always required before starting care?
No. It is most useful when the result can change management, especially with neurological deficit, warning signs or persistent symptoms.
Does sciatica automatically mean a herniated disc?
No. A disc herniation is common, but stenosis, foraminal irritation or another condition can produce a similar pattern.
Is bed rest recommended?
Prolonged bed rest is generally discouraged. Modified and gradually increased activity is usually preferred when neurological findings remain stable.
When is urgent assessment required?
With a new bladder or bowel change, saddle numbness, major or rapidly progressive weakness, fever or significant trauma.
Main clinical sources
- NICE – Low back pain and sciatica in over 16s
- World Health Organization – Guideline for non-surgical management of chronic primary low back pain
- North American Spine Society – Clinical guidelines
Last editorial review: July 2026. General educational information only.
Dr. Sylvain Desforges, B.Sc., D.O., N.D., osteopath – The Spine Page
Continue researching sciatica
Compare the related guides and return to the pillar page for a complete view of sciatica treatment in Terrebonne.
The Spine Page – The best treatments for your spinal problems – www.thespinepage.com