

Triangular bone at the base of the spine, formed by fused sacral vertebrae and connected to the pelvic bones.
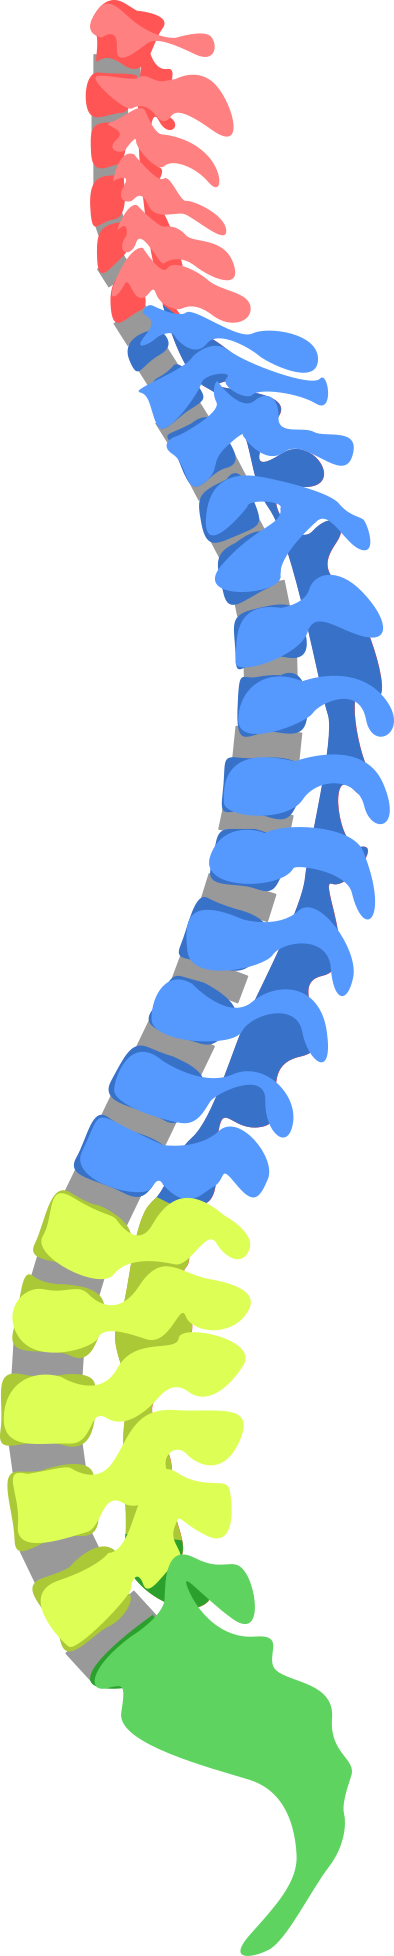
mikeingram1; recoloration : MJL — CC0 1.0. Image source.

Understanding the structure and its role
The sacrum connects the spine to both iliac bones through the sacroiliac joints. Its canal continues the spinal canal, and its foramina transmit sacral nerves. Sacral orientation contributes to pelvic balance. Pain felt over the sacrum may nevertheless arise from the lumbar spine, hip or other tissues.
Symptoms and assessment
Pain after a fall, or pain in a person with osteoporosis, raises the possibility of a sacral fracture that may be difficult to see on plain radiographs. Inflammatory pain or pelvic symptoms require a different approach. Palpation alone cannot establish that the sacrum is displaced.
Assessment considers symptom onset, distribution, restricted activities and medical history. Imaging findings must be compared with the clinical examination: a visible abnormality does not, on its own, establish the source of pain.
Management and outlook
Care depends on the cause: adapted weight-bearing for certain fractures, rehabilitation for mechanical pain or medical referral for inflammatory disease. Forceful techniques are inappropriate when fracture is suspected.
For a mechanical problem without concerning findings, care aims for a gradual return to activity, individually selected exercises and measurable functional goals. Manual care may complement this approach when the examination supports it. Progress is judged through walking, sleep and daily tasks, as well as symptoms, rather than through an image alone.
When to seek prompt assessment
New or progressive weakness, newly impaired walking, loss of sensation around the saddle region, or new bladder or bowel control problems require urgent medical assessment.
Frequently asked questions
Is the sacrum the same as the coccyx?
No. The coccyx is the small terminal structure below the sacrum.
Is sacral pain always sacroiliac pain?
No. Pain location alone cannot identify the responsible tissue.
Can imaging establish the diagnosis alone?
No. Findings must fit the clinical history and examination before they guide treatment.
Should all activity stop?
Usually not: loading is adjusted and gradually increased according to tolerance and the diagnosis.
How should progress be monitored?
Track functional abilities, neurological symptoms and resumed activities so care can be adjusted.
Concept diagram showing key relationships; this is not a scan or an anatomical drawing to scale.
Role of TAGMED care
At TAGMED, this information helps clarify your history, guide assessment and determine whether conservative care is appropriate or medical referral is needed. An anatomical structure, sign or test result is not, by itself, an indication for decompression, laser, shockwave or manual treatment. Care selection depends on the cause of symptoms and your clinical circumstances.
Medical references
- OpenStax, Rice University. Anatomy and Physiology 2e — The Vertebral Column.
- NIAMS, National Institutes of Health. Back Pain: Diagnosis, Treatment, and Steps to Take.
- NIAMS, National Institutes of Health. Ankylosing Spondylitis.
References document the topic; their inclusion does not imply endorsement of TAGMED services by those organizations.
Educational information from The Spine Page. This entry does not replace an individual assessment. Documentary version: October 12, 2026. Sylvain Desforges, B.Sc., D.O., N.D., osteopath and naturopath.
TAGMED clinic contact details
For non-urgent consultations and information about available services.
Clinique TAGMED — Terrebonne
1150, rue Lévis, Suite 200
Terrebonne (Québec) J6W 5S6
450‑704‑4447
Clinique TAGMED — Montréal
1140, avenue Beaumont
Mont-Royal (Québec) H3P 3E5
1‑877‑672‑9060