

Surgery removing some or all of the targeted disc material, particularly to relieve neural compression.
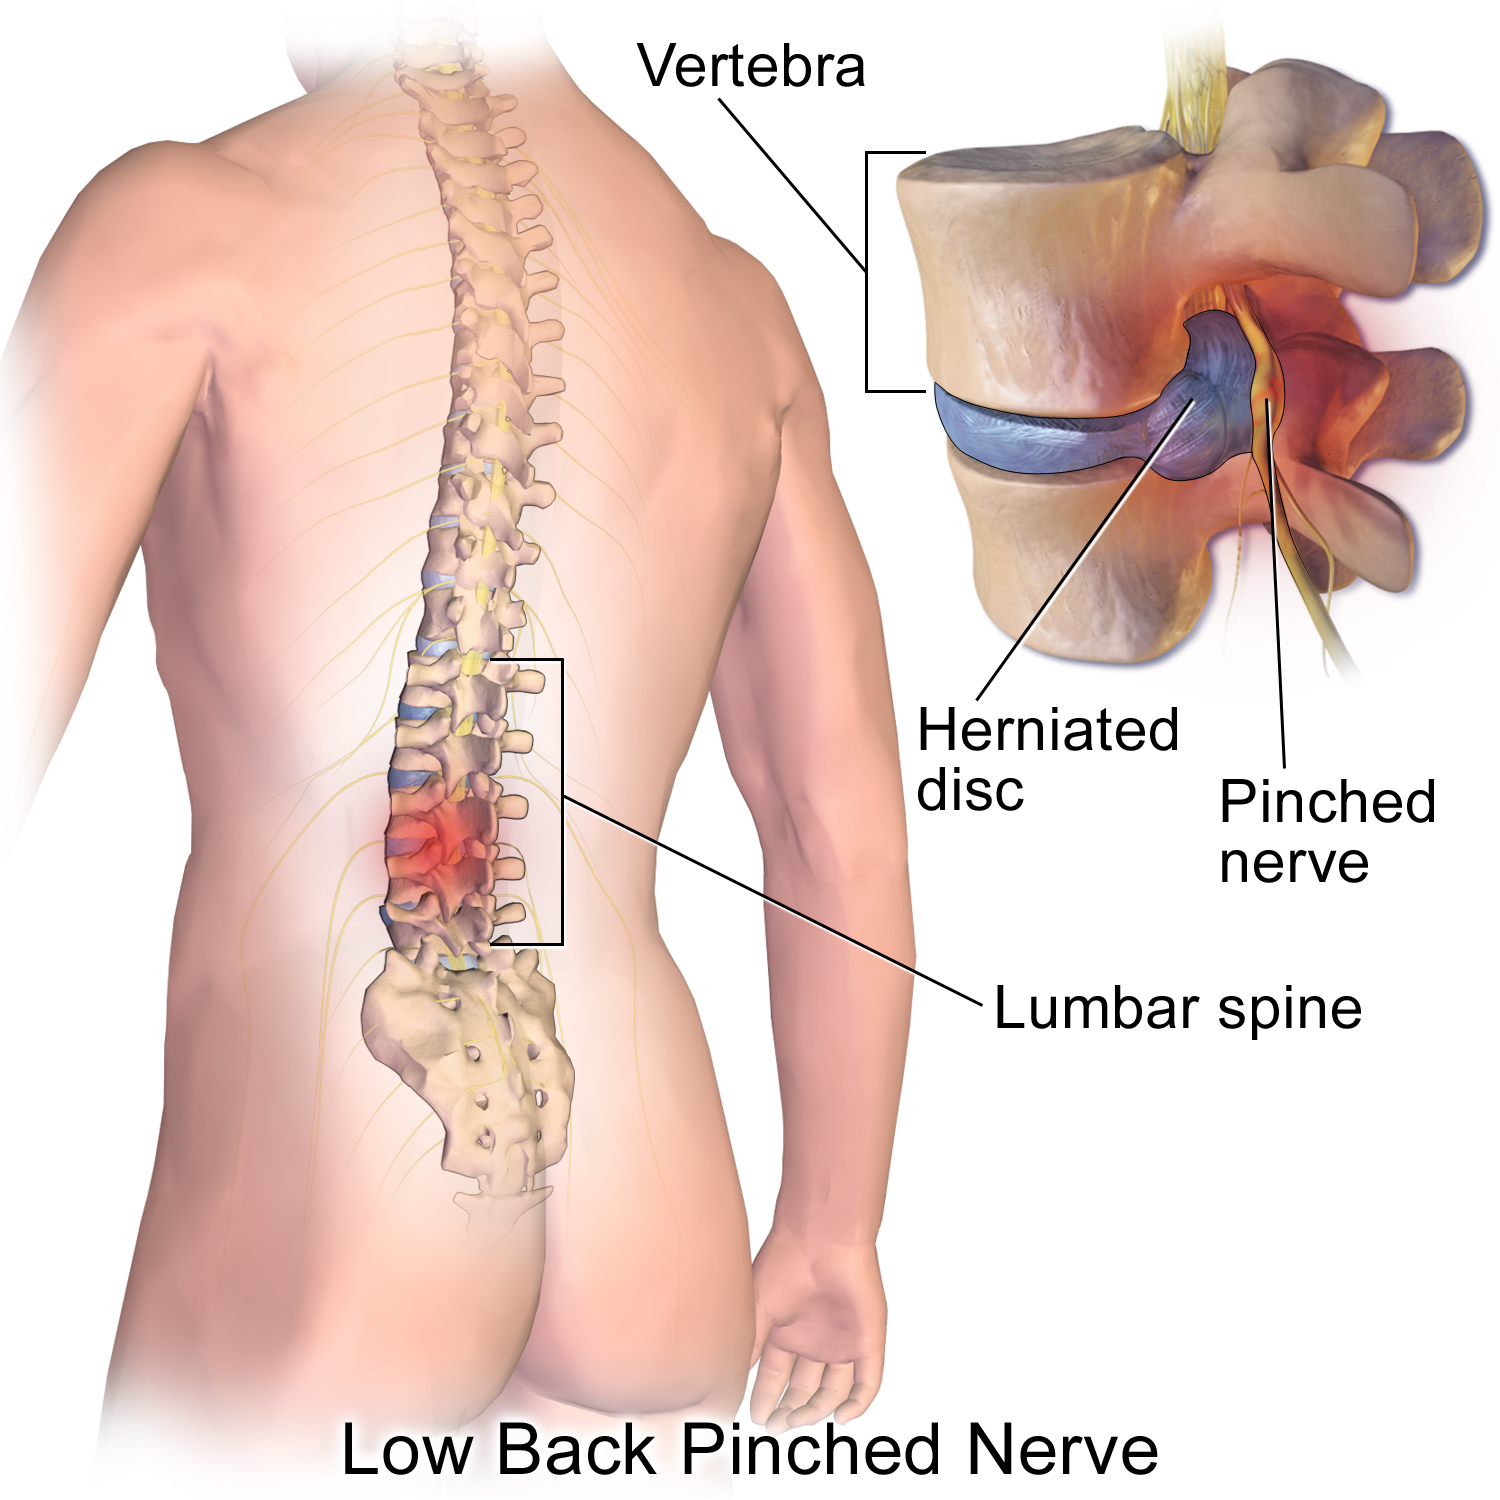
Blausen.com staff (2014), Medical gallery of Blausen Medical 2014, WikiJournal of Medicine 1(2), DOI: 10.15347/wjm/2014.010 — CC BY 3.0. Image source.

Understanding the approach
Discectomy removes disc material compressing a neural structure. For a lumbar herniation it often targets the fragment responsible for leg pain. It does not necessarily mean removing the entire disc or routinely adding a spinal fusion.
Indications and assessment
The decision considers agreement between symptoms, neurological examination and imaging. Persistent disabling radicular pain despite appropriate treatment may justify a surgical discussion. Major or progressive motor weakness and certain cauda equina presentations can change the urgency and require immediate assessment.
Benefits, limitations and precautions
Expected benefit mainly concerns radiating nerve pain; associated back pain or longstanding numbness may persist. Risks include infection, dural tear, nerve injury and recurrent herniation. The favourable natural course of many herniations explains why an abnormal scan alone is insufficient to decide on an operation.
Place in the care pathway
Discectomy is performed by a surgeon, not at TAGMED. Conservative management can precede surgical assessment when the clinical situation permits. After surgery, physical interventions must respect healing and instructions from the team responsible for the operation.
Goals should be practical: walking farther, returning to a chosen activity or reducing symptoms that interfere with sleep. Improvement immediately after an intervention does not establish lasting benefit. Follow-up compares function with the starting point, records adverse effects and considers progress between appointments. An inadequate response should prompt a review of the clinical explanation or proposed approach, rather than an automatic extension of the same treatment.
Before starting, describe the outcome you want, treatments already tried and difficulties encountered. Ask how the response will be measured and when another option would be preferable. Available reports complement the discussion without replacing your current experience, priorities or preferences.
Frequently asked questions
Is the entire disc removed?
Not always. In lumbar surgery the compressive fragment is often the main target.
Is it the same as fusion?
No. Fusion is a separate procedure added only in selected circumstances.
Does the leg recover immediately?
Pain may change quickly, while sensation and strength recover at variable rates.
Can a herniation recur?
Yes. Another fragment can sometimes produce new symptoms.
When is urgent assessment needed?
Progressive weakness, saddle numbness or new urinary changes requires immediate evaluation.
Conceptual diagram of clinical reasoning; not an anatomical drawing to scale.
Role of TAGMED care
This entry describes a medical or specialist option; it does not mean the intervention is performed at TAGMED. The clinic can discuss how its conservative services might fit into coordinated care, considering prescribed treatment, reports and specialist restrictions. Medication should not be stopped or changed on the basis of this page.
Medical references
- AAOS — OrthoInfo. Herniated Disk in the Lower Back.
- NHS. Lumbar decompression surgery.
References document the topic; their inclusion does not imply endorsement of TAGMED services by those organizations.
Educational information from The Spine Page. This entry does not replace an individual assessment. Documentary version: October 12, 2026. Sylvain Desforges, B.Sc., D.O., N.D., osteopath and naturopath.
TAGMED clinic contact details
For non-urgent consultations and information about available services.
Clinique TAGMED — Terrebonne
1150, rue Lévis, Suite 200
Terrebonne (Québec) J6W 5S6
450‑704‑4447
Clinique TAGMED — Montréal
1140, avenue Beaumont
Mont-Royal (Québec) H3P 3E5
1‑877‑672‑9060