





Spinal adhesive arachnoiditis: causes, MRI findings and treatment limits
Spinal adhesive arachnoiditis is a rare chronic inflammatory and scar-forming disorder affecting the arachnoid and nerve roots within the spinal canal. Symptoms and MRI findings may be severe, mild or poorly correlated, and no standardized curative treatment exists.
Inflammation can cause nerve-root clumping, adhesions, impaired cerebrospinal-fluid flow, loculated cysts, arachnoid webs, calcification, tethering and secondary syringomyelia. Reported causes include spinal surgery, infection, haemorrhage, trauma, intrathecal agents and older oil-based contrast materials. Arachnoiditis after modern epidural injection or blood patch is considered rare, and a temporal relationship does not always prove causation.
Assessment and differential diagnosis
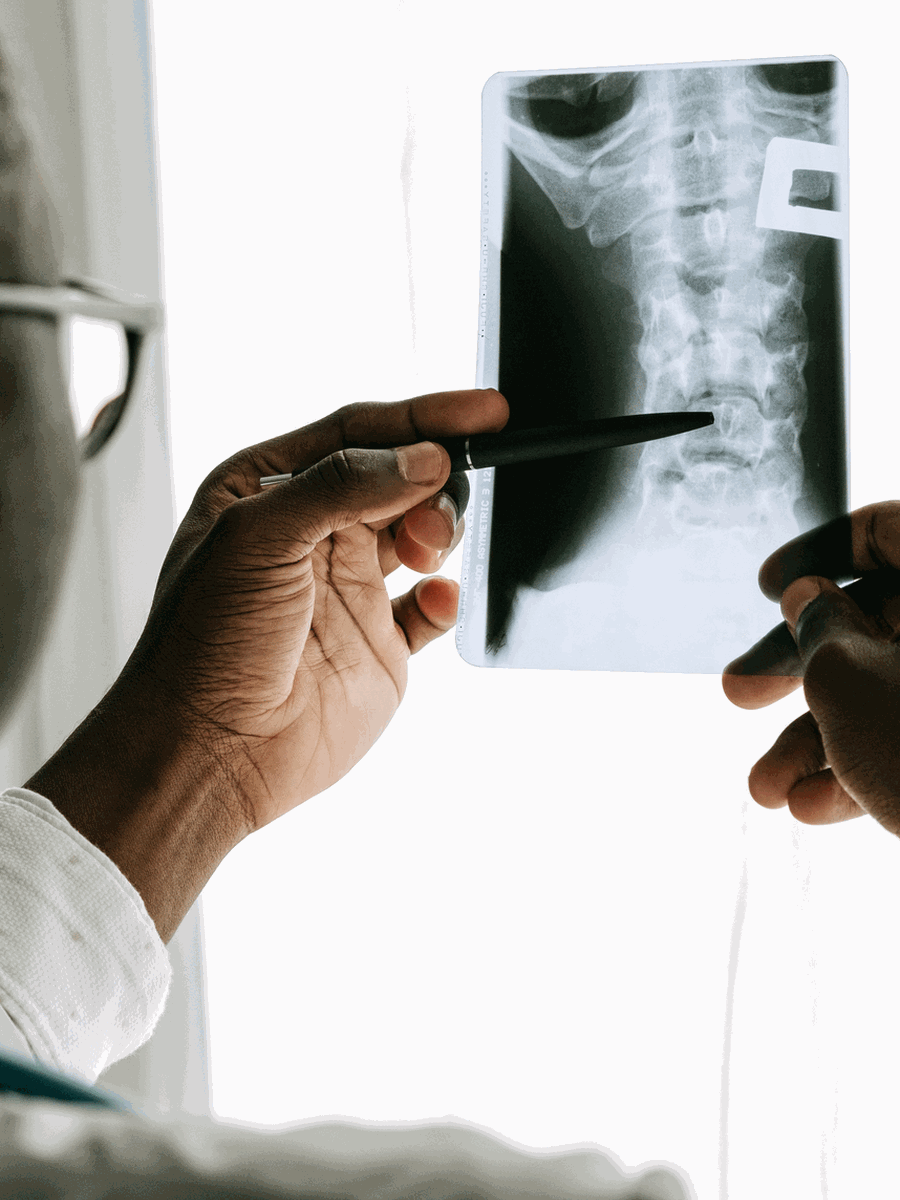
MRI is the principal imaging test. Lumbar patterns include clumped nerve roots, an empty-thecal-sac appearance with roots adherent to the periphery and a soft-tissue mass replacing normal root distribution. In the thoracic or cervical spine, adhesions may cause cord distortion, arachnoid cysts, webs or syringomyelia. Contrast may show meningeal or root enhancement in active inflammation but is not always present. CT myelography can demonstrate block or loculation when MRI is limited. The diagnosis requires a compatible clinical history and exclusion of recurrent disc disease, stenosis, tumour, infection, demyelinating disease and other causes.
| Clinical pattern | Possible next step | Why it matters |
|---|---|---|
| Incidental MRI pattern without concordant symptoms | Observation and alternative diagnosis review | Radiology alone does not establish symptomatic disease. |
| Chronic pain and stable neurological findings | Multimodal pain and rehabilitation plan | The goal is function and symptom control. |
| Progressive myelopathy, syringomyelia or focal CSF block | Specialist neurosurgical assessment | Selected focal adhesions may be surgically treatable. |
| New bladder, bowel or major motor dysfunction | Urgent assessment | A separate compressive emergency must be excluded. |


Treatment and decision-making
There is no universally effective medication or operation. Management may include education, graded rehabilitation, neuropathic-pain medication, sleep and psychological care, pelvic-floor or bladder management and multidisciplinary pain treatment. Repeated invasive spinal procedures should be considered cautiously because additional inflammation or scarring is possible. Surgical arachnoidolysis, cyst fenestration, duraplasty, shunting or treatment of syringomyelia may be considered for focal progressive disease, but surgery is technically difficult and recurrence is common. The aim may be stabilization rather than complete cure.
How to interpret the condition in practice
Arachnoiditis should not become a catch-all explanation for every symptom after surgery or injection. The diagnosis is strongest when the history, neurological pattern and characteristic imaging agree and competing treatable lesions have been excluded.
Reconstruct the exposure history
Surgery, infection, haemorrhage and intrathecal agents are important.
Map the neurological level
Lumbar root symptoms differ from thoracic cord disease.
Review CSF-flow effects
Cysts and syringomyelia may be more clinically important than pain alone.
Avoid assuming causation
A recent injection and an MRI change do not automatically prove cause.
Limit repeated procedures
Additional invasive interventions may worsen scarring in theory.
Set realistic goals
Stabilization and functional adaptation may be more achievable than cure.
How to monitor the condition and avoid interpretation errors
A credible plan should define what improvement means before treatment begins and should explain how the diagnosis will be reconsidered if the expected response does not occur. Pain intensity can change independently from neurological function, walking tolerance, sleep or participation. For uncommon conditions, progression and safety are often more important than day-to-day symptom fluctuation.
Create a baseline
Record symptom distribution, strength, sensation, walking, sleep, medication use and the activities that matter most.
Use a planned review point
Decide when the response will be reviewed rather than continuing automatically until a treatment package is completed.
Separate relief from diagnosis
Temporary improvement after medication, injection, manual care or a device does not prove the proposed structure was the true cause.
Watch the neurological trajectory
New weakness, spreading numbness, gait change or autonomic symptoms matter even if pain decreases.
Review alternative causes
Degenerative, inflammatory, infectious, oncological and postoperative mechanisms may overlap.
Escalate proportionately
Imaging, specialist referral or surgery should be considered when the risk or functional loss justifies it.
Common errors to avoid
- Treating the most unusual imaging finding instead of the clinically relevant lesion.
- Assuming that a stable imaging abnormality explains a changing symptom pattern.
- Using one negative test to exclude a condition that remains clinically plausible.
- Repeating passive treatment despite no measurable functional progress.
- Generalizing results from a small specialist series to every person with the same label.
- Delaying urgent assessment to complete a predetermined number of visits.
Shared decision-making is strongest when uncertainty is stated directly. A provider should explain what is confirmed, what remains probable, which alternatives still matter and what findings would change the plan. For rare or controversial diagnoses, a second opinion from a clinician experienced with the specific condition may be more useful than adding another non-specific treatment.
Questions before choosing care
What is the leading diagnosis?
Ask which symptoms and examination findings support it.
What alternative remains possible?
Common competing causes should be reviewed before an invasive procedure.
What test changes management?
Avoid testing or imaging that cannot alter the next step.
What outcome matters?
Track function, neurological safety and meaningful activity.
A single symptom, image or treatment response rarely establishes the complete cause by itself.
Relevant specialized resources
Some resources may share ownership or editorial direction; this relationship is disclosed and the links are included for contextual relevance.
Frequently asked questions
Is adhesive arachnoiditis common?
No. It is considered rare.
Can it occur after spine surgery?
Yes.
Can epidural injections cause it?
It has been reported rarely, but causation is difficult to establish.
What does nerve-root clumping mean?
The roots adhere together rather than floating separately in cerebrospinal fluid.
Can MRI findings exist without symptoms?
Yes.
Can symptoms occur with limited MRI change?
Yes.
Is there a cure?
No standardized curative treatment exists.
Can surgery help?
Selected focal progressive cases may benefit, but recurrence and complications are important.
Can spinal cord stimulation be used?
It may be considered for selected chronic neuropathic pain after specialist assessment.
Does The Spine Page diagnose arachnoiditis?
No.
Sources consulted
- Zhang et al. — Systematic review of spinal adhesive arachnoidopathy
- Maillard et al. — Spinal adhesive arachnoiditis literature review
- Eisenberg et al. — Arachnoiditis after lumbar epidural injections
- Villani et al. — Arachnoiditis after epidural blood patch
Last editorial review: July 2026. General educational information only.
Dr. Sylvain Desforges, B.Sc., D.O., N.D., osteopath — The Spine Page
Continue exploring spine health
Use the condition and treatment hubs to compare related guides.
The Spine Page — The best treatments for your spinal problems — www.thespinepage.com
Topic index: Other spinal conditions
Explore this topic cluster by search intent. Each link leads to a distinct guide directly related to the subject.